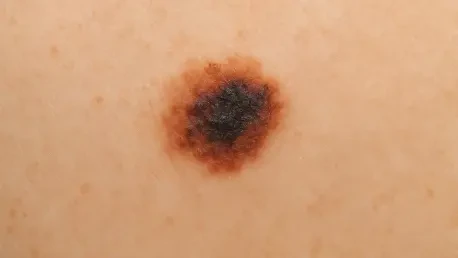

While artificial intelligence has matched the accuracy of human specialists in controlled environments, its clinical utility depends on how well it integrates into existing primary care infrastructure. In the United Kingdom, where healthcare resources are perpetually balanced against rising demand, the deployment of diagnostic algorithms is no longer a distant prospect but a current reality in 2026. As melanoma rates continue to climb due to changing environmental factors and an aging population, the burden placed on general practitioners to act as flawless gatekeepers has reached a critical threshold. The visual complexity of early-stage skin cancer often makes triage a daunting task, even for experienced clinicians. Consequently, the recent findings published in the British Journal of Cancer regarding public sentiment toward AI-assisted diagnosis provide an essential foundation for the next phase of medical technology. This research moves beyond superficial polling, offering a detailed analysis of how patients perceive the intersection of machine learning and clinical expertise. By examining the nuances of patient trust and the conditions under which algorithmic tools are deemed acceptable, the study establishes a framework for integrating digital health solutions that honor the patient-doctor relationship while maximizing the benefits of computational precision.
Designing the Evaluation Framework
Part 1: The Discrete Choice Experiment Methodology
To move beyond abstract opinions and gauge how individuals would react in real-world clinical settings, researchers utilized a discrete choice experiment. This sophisticated econometric tool forces participants to make difficult trade-offs between various service features, mirroring the actual decisions patients face when seeking medical care. In this study, respondents were presented with hypothetical scenarios that varied across five critical attributes: the location of the assessment, the specific role of the artificial intelligence, the level of diagnostic accuracy, the speed of the decision, and the degree of human oversight. By requiring participants to choose one scenario over another, the methodology allowed researchers to quantify the latent preferences of the British public. This approach revealed which factors are truly non-negotiable and which ones patients are willing to compromise on in exchange for better health outcomes. The resulting data provides a much clearer picture of public priorities than a traditional survey, highlighting the specific service configurations that the population finds trustworthy and acceptable during the diagnostic process.
Part 2: Statistical Modeling of Patient Trade-Offs
The analytical power of the discrete choice experiment lies in its ability to assign a numerical value to different service components, essentially mapping the “utility” that each feature provides to the patient. For instance, the research could determine whether a patient would prefer a slightly less accurate result that is delivered instantly at a local pharmacy versus a highly accurate result that requires a two-week wait at a specialized hospital. By analyzing thousands of these individual choices, the study identified a clear hierarchy of needs within the primary care ecosystem. It became evident that the public does not view artificial intelligence as a monolithic entity but as a tool whose value is entirely dependent on its implementation. This granular understanding is vital for developers who often focus solely on the technical metrics of an algorithm without considering the logistical and emotional environment of the general practitioner’s office. The findings suggest that the most successful technological adoptions will be those that align with the established expectations of the healthcare journey, rather than attempting to radically disrupt them without a clear mandate from the users themselves.
Core Preferences and Public Consensus
Part 1: The Indispensable Nature of Human Oversight
A primary finding of the research is the unwavering public insistence on a “human-in-the-loop” model for medical diagnostics. The vast majority of participants expressed a strong preference for scenarios where the artificial intelligence acts as a supportive tool for a doctor rather than an autonomous decision-maker. For a condition as serious as melanoma, where a diagnostic error can have life-altering or even fatal consequences, patients continue to value the accountability and nuanced judgment that only a trained clinician can provide. This sentiment stems from a deep-seated belief that while machines are excellent at pattern recognition, they lack the contextual understanding and empathy required to navigate a cancer diagnosis. There is a palpable hesitancy toward any system that appears to bypass the clinical judgment of a physician, suggesting that the public sees the doctor as the ultimate safeguard against the potential hallucinations or biases of an algorithmic system. For the healthcare industry, this means that the road to AI adoption must be paved with collaboration rather than replacement, ensuring that the physician remains the central figure in the patient’s care pathway.
Part 2: Clinical Judgment versus Algorithmic Autonomy
The resistance to autonomous AI systems highlights a significant cultural barrier that technology developers must address through transparency and education. Patients are often concerned that a fully automated process would treat them as a set of data points rather than an individual with a unique medical history and personal anxieties. The study showed that even when an algorithm is presented as statistically superior to a human in terms of raw detection rates, the absence of a doctor’s confirming voice significantly reduces patient confidence in the result. This indicates that trust is not solely a function of mathematical reliability but is also built on the foundation of the therapeutic relationship. In 2026, as the NHS continues to integrate sophisticated software into its workflow, maintaining this human connection will be essential for ensuring that patients follow through with recommended treatments and referrals. The challenge for modern medicine is to leverage the speed and precision of high-end computing without eroding the sense of security that comes from a face-to-face consultation with a medical professional who is ultimately responsible for the outcome.
Part 3: Prioritizing Diagnostic Accuracy Over Speed
In many areas of consumer technology, speed is the primary metric of success, with users demanding instant gratification and rapid service delivery. However, the context of cancer diagnosis presents a very different set of priorities for the British public. The research indicates that patients overwhelmingly prioritize diagnostic accuracy over the speed at which a result is generated. While artificial intelligence is often promoted as a way to accelerate the triage process and reduce wait times, the public views its primary value as a means of improving the reliability of a diagnosis. This finding is particularly relevant for the design of primary care services, as it suggests that patients are generally willing to accept longer wait times if they are guaranteed a more accurate and thorough evaluation. The trade-off analysis performed during the study confirmed that accuracy was the most heavily weighted attribute in the participants’ decision-making process. This preference suggests that the marketing of medical AI should shift its focus from “fast results” to “higher-quality care,” aligning the technology’s value proposition with the actual desires of the population it serves.
Part 4: Patient Willingness to Accept Wait Times
The willingness of patients to endure longer wait times for the sake of accuracy provides a clear mandate for how triage systems should be structured in the current healthcare environment. If a new AI tool can significantly reduce the rate of false negatives—cases where cancer is present but missed—patients are likely to support its use even if it adds extra steps to the diagnostic journey. This patience reflects a sophisticated understanding of the stakes involved in oncology, where the consequences of a missed early-stage melanoma are far more severe than the inconvenience of a delayed referral. Furthermore, the study suggests that the anxiety associated with waiting for a diagnosis can be mitigated if the patient believes the process is more robust and comprehensive. By using AI as a “second reader” or an expert auditor, clinicians can provide patients with a dual-layered assurance that their health is being evaluated with the best available human and machine expertise. This redundancy is perceived as a significant benefit, providing a level of psychological comfort that a single-source diagnosis, whether human or machine, may not be able to offer on its own.
Demographic Factors and Implementation Strategies
Part 1: The Impact of Technological Familiarity
While the general trend toward AI acceptance is positive, the research identified significant variations in attitude based on an individual’s level of technological familiarity. Those who regularly interact with advanced technology in their daily lives, such as users of digital assistants or algorithmic financial services, tend to view medical AI with a much higher degree of confidence. This familiarity seems to demystify the technology, moving the public perception away from science-fiction tropes of “robot doctors” toward a more realistic view of AI as specialized medical software. For these digital natives, the integration of an algorithm into a skin check is seen as a logical extension of the modernization occurring in every other sector of society. Conversely, individuals who are less comfortable with digital tools may harbor more skepticism, fearing that the technology will lead to a more impersonal and confusing healthcare experience. Recognizing these differences is essential for the effective rollout of new diagnostic tools, as it highlights the need for tailored communication strategies that address the specific concerns of different demographic groups.
Part 2: Navigating the Digital Divide in Primary Care
The divide in technological acceptance suggests that a “one-size-fits-all” approach to implementing AI in primary care will likely encounter localized resistance. To ensure equitable access and trust, healthcare providers must develop inclusive implementation strategies that provide extra support and clear explanations for those who may be wary of algorithmic tools. This could involve the use of educational materials that explain how the AI works in plain language, emphasizing its role as an assistant to the doctor rather than a replacement. Furthermore, the study noted that prior experience with the healthcare system, particularly among those who have previously undergone skin checks or dealt with cancer services, often leads to a more nuanced appreciation for tools that can improve the triage process. These patients have firsthand knowledge of the pressures on the NHS and are often more receptive to innovations that promise to make the system more efficient and reliable. By leveraging the positive experiences of these patients, health services can build a broader consensus and demonstrate the tangible benefits of AI-enhanced care to the wider public.
Part 3: Strategic Directions for the National Health Service
As the National Health Service navigates the complexities of the mid-2020s, the integration of AI triage tools offers a vital solution for managing the diagnostic backlog and specialist shortages. However, the research provides a clear warning that the technical validation of an algorithm is only the first step in a successful implementation. To achieve true social validation, policymakers and health service designers must ensure that these tools are deployed in a way that remains deeply rooted in patient-centered care. The researchers established that the public is ready to embrace the future of AI-augmented medicine, but only if the technology is used to enhance the existing clinical relationship rather than automate it out of existence. The study determined that the most effective path forward involves treating artificial intelligence as a “digital stethoscope”—a powerful instrument in the hands of a trusted clinician that improves the detection of life-threatening conditions while maintaining the human touch. Policymakers observed that by focusing on transparency, accuracy, and human oversight, the UK can lead the way in creating a diagnostic pathway that is both technologically advanced and socially acceptable. These findings indicated that the long-term success of medical AI will be measured not just by its detection rates, but by the level of trust it fosters within the community it serves.